
Kienbock's Disease on MRI & X-ray: Imaging Findings
Kienbock's disease is avascular necrosis of the lunate bone, the central keystone of the proximal carpal row. The lunate has a tenuous blood supply, making it vulnerable to ischemic injury from repetitive trauma, ulnar minus variance, or vascular anatomic variants. The disease progresses through stages defined by the Lichtman classification, from marrow edema through sclerosis, fragmentation, collapse, and ultimately carpal arthritis. MRI is the most sensitive modality for early detection and staging, often revealing signal changes before X-ray abnormalities appear.
Common Symptoms
- Central dorsal wrist pain localized directly over the lunate bone
- Decreased wrist range of motion, particularly extension and radial deviation
- Progressively worsening grip strength over months to years
- Wrist swelling and point tenderness over the lunate on palpation
- Stiffness that worsens with activity and does not resolve with rest in advanced stages
- Pain with axial wrist loading activities such as push-ups or weight-bearing through the palm
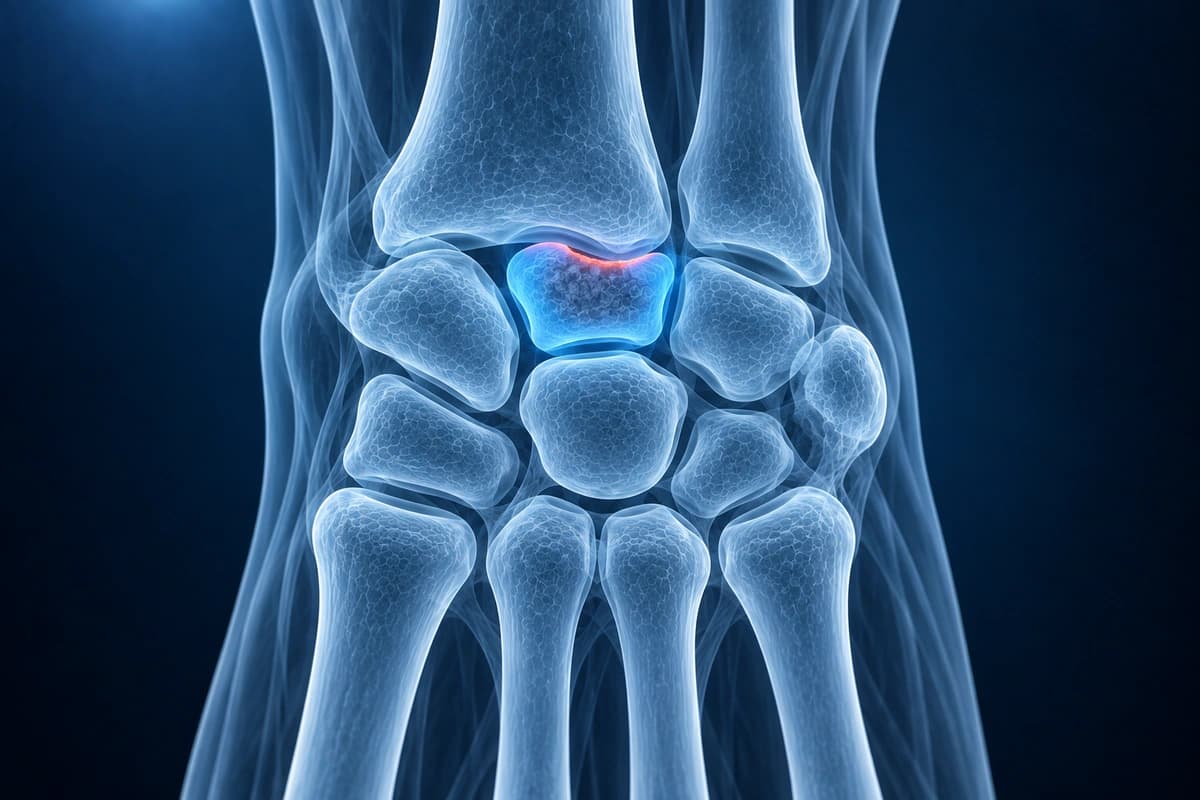
Kienbock's Disease Radiology: Lichtman Signs on X-ray and MRI
Radiologists stage Kienbock's disease with the Lichtman system, based on how the lunate looks. In stage I the X-ray is normal or shows only a fracture line, while MRI already shows abnormal signal in the lunate. Stage II adds increased bone density, stage III collapse of the lunate, and stage IV arthritis in the surrounding wrist joints.
Imaging signs at each Lichtman stage
- Stage I: a normal X-ray or a thin fracture line; MRI shows low T1 signal spread through the lunate.
- Stage II: the lunate looks whiter and denser on X-ray but keeps its normal size and shape.
- Stage IIIA: the lunate collapses or fragments, while the other carpal bones stay aligned.
- Stage IIIB: lunate collapse plus a fixed, flexed scaphoid and loss of carpal height as the neighbouring bones shift.
- Stage IV: degenerative arthritis of the radiocarpal or midcarpal joints around the collapsed lunate.
What else the radiologist checks
The report often notes ulnar variance, whether the ulna ends shorter than the radius, because negative ulnar variance is associated with the disease. Contrast-enhanced MRI can show whether parts of the lunate still have a blood supply, which newer treatment algorithms combine with the Lichtman stage. Other conditions can mimic Kienbock's disease on MRI, so the pattern of change across the lunate matters. For treatment options stage by stage, read the Lichtman staging guide.
Questions about your lunate imaging
- Which Lichtman stage does my imaging show?
- Is my ulnar variance negative, neutral or positive?
- Does the lunate still have a blood supply on contrast MRI?
- Has the lunate collapsed, and are the other carpal bones still aligned?
What We Look For on Imaging
- Diffuse low T1 signal throughout the lunate indicating marrow replacement
- Variable T2 signal depending on disease stage (edema versus sclerosis)
- Lunate height loss, flattening, or fragmentation
- Coronal fracture line through the lunate body
- Secondary carpal collapse with scaphoid flexion and capitate proximal migration
- Ulnar variance measurement and radiocarpal arthritic changes
Frequently Asked Questions
What are the Lichtman staging criteria for Kienbock's disease and their treatment implications?
The Lichtman classification defines disease progression: Stage I shows normal radiographs with MRI evidence of marrow edema as decreased T1 and elevated T2 signal in the lunate. Stage II demonstrates lunate sclerosis on radiograph without height loss. Stage IIIA presents with lunate collapse but preserved carpal alignment. Stage IIIB adds fixed scaphoid flexion and proximal capitate migration. Stage IV includes generalized radiocarpal and midcarpal osteoarthritis. Treatment is stage-dependent: Stage I to II may benefit from immobilization or revascularization, Stages II to IIIA from joint leveling procedures when ulnar minus variance is present, Stage IIIB from limited carpal fusion such as scaphocapitate or scaphotrapeziotrapezoid fusion, and Stage IV from proximal row carpectomy or total wrist fusion. AI can help explain these stages, but a hand surgeon must confirm the stage and discuss which treatments are appropriate for you.
How does ulnar variance influence the development and surgical treatment of Kienbock's disease?
Ulnar minus variance, defined as the ulna being shorter than the radius by more than 1 mm on a standardized PA radiograph with the forearm in neutral rotation, concentrates compressive load from the radius onto the radiolunate articulation and reduces the force-sharing role of the TFCC. This anatomic variant is present in approximately 75% of Kienbock's patients compared to 20% of the general population. Joint leveling procedures including radial shortening osteotomy or ulnar lengthening osteotomy equalize the load distribution, reducing compression on the ischemic lunate.
Why is MRI superior to CT and plain radiographs for early Kienbock's disease?
MRI detects Stage I Kienbock's disease by identifying bone marrow edema as decreased T1 and increased T2 signal before any structural abnormality is visible on radiograph or CT. This early detection window is therapeutically critical because intervention before lunate collapse, particularly joint leveling in the presence of ulnar minus variance or revascularization procedures, has substantially better outcomes than treatment after Stage IIIA collapse. CT is complementary for evaluating the presence and degree of coronal fracture lines within the lunate and for surgical planning but cannot detect the pre-collapse vascular compromise that MRI reveals. Gadolinium-enhanced MRI can also assess residual lunate vascularity by demonstrating enhancement in viable bone.
Sources
- Lichtman DM, Mack GR, MacDonald RI, Gunther SF, Wilson JN. Kienböck's disease: the role of silicone replacement arthroplasty. J Bone Joint Surg Am. 1977;59(7):899-908.
- Lichtman DM, Lesley NE, Simmons SP. The classification and treatment of Kienbock's disease: the state of the art and a look at the future. J Hand Surg Eur Vol. 2010;35(7):549-554.
- Arnaiz J, Piedra T, Cerezal L, et al. Imaging of Kienböck disease. AJR Am J Roentgenol. 2014;203(1):131-139.
- Lichtman DM, Pientka WF 2nd, Bain GI. Kienböck disease: a new algorithm for the 21st century. J Wrist Surg. 2017;6(1):2-10.
- Stahl S, Stahl AS, Meisner C, et al. Critical analysis of causality between negative ulnar variance and Kienböck disease. Plast Reconstr Surg. 2013;132(4):899-909.
- Gelberman RH, Salamon PB, Jurist JM, Posch JL. Ulnar variance in Kienböck's disease. J Bone Joint Surg Am. 1975;57(5):674-676.
- American Academy of Orthopaedic Surgeons. Kienböck's Disease. OrthoInfo.
Related Articles
Lichtman stages I–IV of Kienbock disease — lunate avascular necrosis, MRI signal evolution, fragmentation, collapse, and treatment by stage.
Learn when 3T wrist MRI can help for TFCC tears, scapholunate ligament injury, occult scaphoid fracture, and cartilage detail, and when X-ray or 1.5T MRI is enough.
Decode your wrist MRI report including TFCC evaluation, scaphoid fracture detection, and carpal tunnel findings.
Understand your imaging before your next appointment
MRI, X-ray or CT from a CD, folder or ZIP. A PDF report or photos of the films work too.
Free to open and preview, no account needed. An optional AI report from $10 explains your images in plain language, with questions for your doctor.
Your raw files stay on this device. Only rendered images and minimal context are sent when you request an AI report.
Medical Disclaimer: This page is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. AI-generated analysis may contain errors. Always consult a qualified healthcare professional for medical decisions. Full Disclaimer