
De Quervain's Tenosynovitis on MRI & X-ray: Imaging Findings
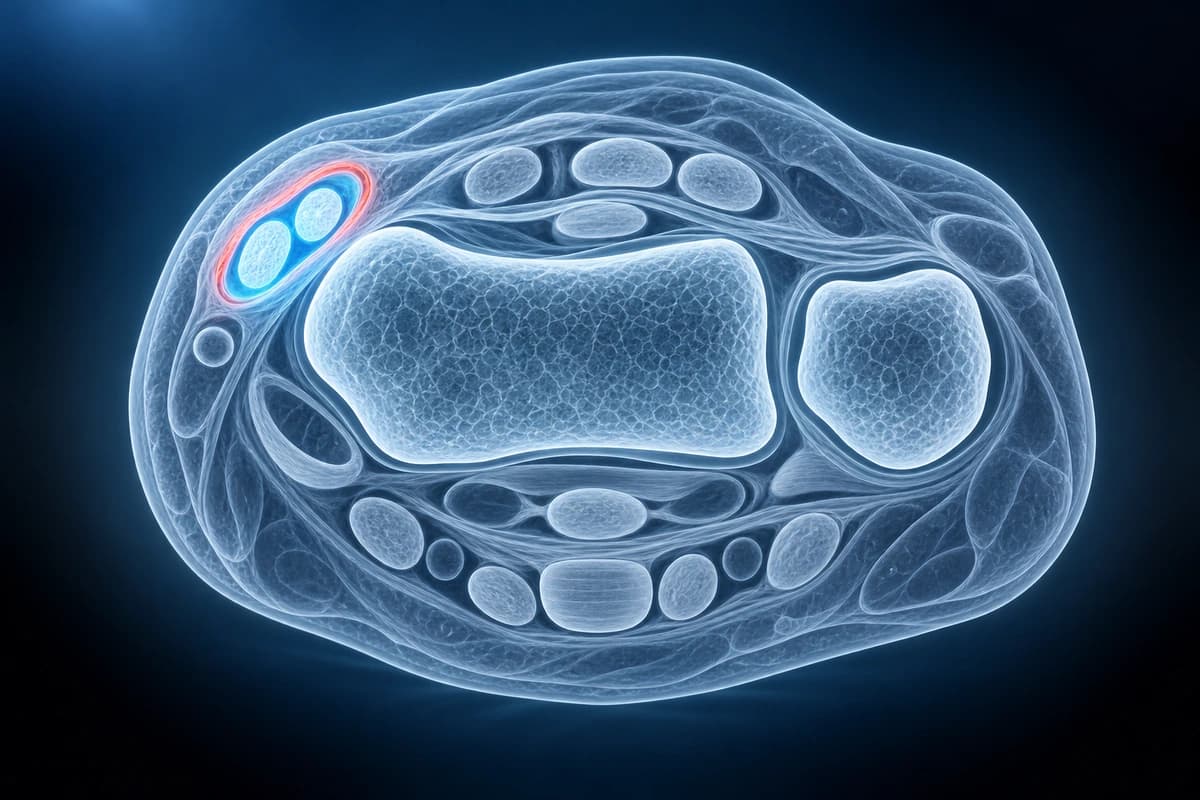
De Quervain's tenosynovitis is a painful condition affecting the first dorsal compartment of the wrist, involving the abductor pollicis longus (APL) and extensor pollicis brevis (EPB) tendons as they pass over the radial styloid. It is commonly triggered by repetitive thumb and wrist movements and is particularly prevalent in new parents, manual laborers, and racquet sport athletes. MRI and ultrasound are valuable for confirming the diagnosis, evaluating tendon sheath thickening, identifying subcompartment septation, and ruling out other causes of radial-sided wrist pain.
Common Symptoms
- Pain along the radial side of the wrist at the base of the thumb and over the radial styloid
- Swelling and tenderness directly over the first dorsal extensor compartment
- Pain with thumb gripping, pinching, or wringing motions such as lifting an infant
- Positive Finkelstein test with pain reproduced by ulnar deviation of the wrist with the thumb enclosed in the fist
- Crepitus or snapping sensation over the radial styloid with thumb movement
- Difficulty with activities requiring thumb opposition such as opening jars or turning keys
What We Look For on Imaging
- Thickening of the first dorsal compartment extensor retinaculum
- Fluid within the tendon sheath surrounding the APL and EPB tendons
- Tendon thickening and increased signal indicating tendinopathy
- Peritendinous and subcutaneous edema around the radial styloid
- Septation within the first dorsal compartment (separate EPB subcompartment)
- Bone marrow edema in the radial styloid in severe or chronic cases
Frequently Asked Questions
Why does first dorsal compartment subcompartment septation affect treatment outcomes?
Up to 30% of individuals have a fibrous or bony septum creating a separate subcompartment for the extensor pollicis brevis tendon within the first dorsal compartment. When a corticosteroid injection is placed into the main compartment containing the abductor pollicis longus, the EPB subcompartment may not be reached, explaining failure rates of approximately 30% when septation is present compared to less than 10% without septation. MRI or ultrasound can identify septation preoperatively, guiding whether a two-compartment injection technique or surgical release with deliberate opening of both subcompartments is required.
How does MRI distinguish De Quervain's tenosynovitis from other causes of radial wrist pain?
MRI directly visualizes the first dorsal compartment extensor retinaculum thickening, fluid surrounding the APL and EPB tendons, peritendinous and subcutaneous edema around the radial styloid, and tendon signal abnormality indicating tendinopathy. Importantly, MRI simultaneously evaluates the scaphoid for fracture or nonunion, the first CMC joint for osteoarthritis, the intersection zone at the second dorsal compartment crossing for intersection syndrome, and the superficial radial nerve for Wartenberg syndrome. This differential evaluation is critical because radial-sided wrist pain has numerous causes with distinct treatments, and De Quervain's is a clinical diagnosis that imaging can confirm or refute.
What are the treatment options for De Quervain's tenosynovitis in order of invasiveness?
First-line management includes thumb spica splinting maintaining the wrist and thumb in neutral, anti-inflammatory medication, and activity modification avoiding repetitive pinching and twisting. Corticosteroid injection into the first dorsal compartment achieves resolution in 70-90% of primary cases. When septation is present, ultrasound-guided dual-compartment injection improves success rates. Surgical first dorsal compartment release is reserved for cases failing two to three injections and is highly effective with low recurrence. MRI findings of severe tendon degeneration or large subcompartment septation support earlier consideration of surgical release over repeated injection.
Sources
- Ilyas AM, Ast M, Schaffer AA, Thoder J. De Quervain tenosynovitis of the wrist. J Am Acad Orthop Surg. 2007;15(12):757-764.
- Richie CA 3rd, Briner WW Jr. Corticosteroid injection for treatment of de Quervain's tenosynovitis: a pooled quantitative literature evaluation. J Am Board Fam Pract. 2003;16(2):102-106.
- Bernstein DT, Gonzalez MA, Hendrick RG, et al. Impact of septated first dorsal compartments on symptomatic de Quervain disease. Plast Reconstr Surg. 2019;144(2):389-393.
- American Academy of Orthopaedic Surgeons. De Quervain's Tenosynovitis. OrthoInfo.
Understand your imaging before your next appointment
MRI, X-ray or CT from a CD, folder or ZIP. A PDF report or photos of the films work too.
Free to open and preview, no account needed. An optional AI report from $10 explains your images in plain language, with questions for your doctor.
Your raw files stay on this device. Only rendered images and minimal context are sent when you request an AI report.
Medical Disclaimer: This page is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. AI-generated analysis may contain errors. Always consult a qualified healthcare professional for medical decisions. Full Disclaimer