
Ganglion Cyst on MRI & X-ray: Imaging Findings
Ganglion cysts are the most common soft tissue masses of the wrist and hand, accounting for 60-70% of all hand and wrist masses. These benign, fluid-filled lesions arise from joint capsules, tendon sheaths, or ligaments, with the most common location being the dorsal wrist originating from the scapholunate ligament. Volar wrist ganglia typically arise from the radiocarpal or scaphotrapezial joint. MRI is the gold standard for confirming the diagnosis, mapping the cyst stalk to its origin, evaluating the relationship to adjacent neurovascular structures, and ruling out other soft tissue masses.
Common Symptoms
- Visible or palpable lump on the dorsal or volar wrist that may fluctuate in size
- Wrist pain that worsens with repetitive activity, loading, or sustained positions
- Aching discomfort that may extend into the forearm or hand
- Weakness in grip strength attributable to pain inhibition
- Numbness or tingling when the cyst compresses an adjacent nerve such as the superficial radial nerve
- Dorsal wrist pain without a palpable mass in occult ganglion presenting as unexplained wrist pain
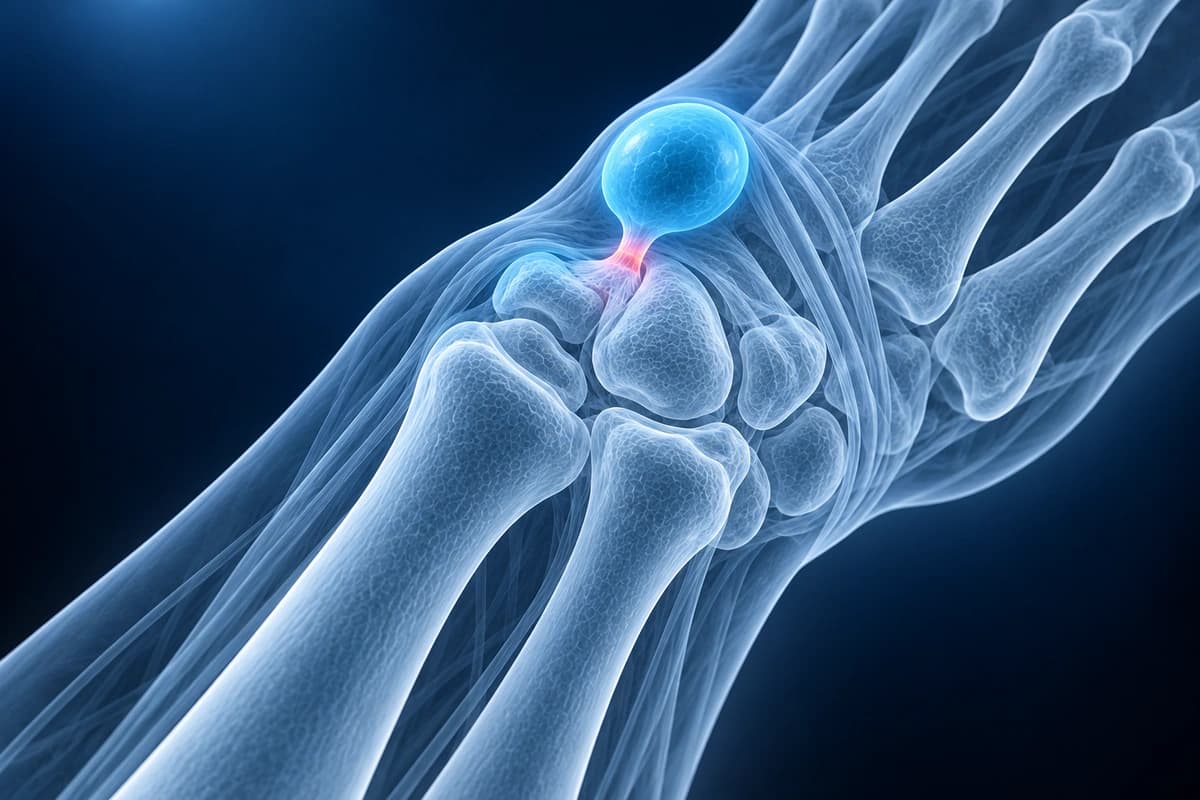
What We Look For on Imaging
- Well-defined cystic lesion with uniformly high T2 and low T1 signal
- Thin, smooth wall without solid components or internal enhancement
- Stalk or pedicle connecting the cyst to its joint or ligament of origin
- Relationship to the scapholunate ligament for dorsal wrist ganglia
- Proximity to the radial artery for volar wrist ganglia
- Multiloculated or septated morphology in complex ganglia
Frequently Asked Questions
What MRI features confirm a ganglion cyst and differentiate it from other wrist masses?
A ganglion cyst demonstrates homogeneously high T2 signal equivalent to fluid, uniformly low T1 signal, a thin smooth non-enhancing wall, and the absence of solid internal components or nodularity on gadolinium-enhanced sequences. The stalk or pedicle connecting the cyst to its joint or ligament of origin, most commonly the scapholunate ligament for dorsal ganglia and the radiocarpal or scaphotrapezial joint for volar ganglia, confirms the diagnosis and is critical for surgical planning to prevent recurrence. Giant cell tumor of the tendon sheath, lipoma, and rare malignant soft tissue sarcomas can all mimic ganglia clinically but show distinct MRI signal characteristics and enhancement patterns. AI can offer an educational description of the images, but it cannot confirm that a lump is a benign ganglion or rule out another cause. A clinician must assess the lump and confirm the diagnosis.
What is an occult ganglion and why is it clinically important?
An occult ganglion is a small intra-articular or periligamentous cyst that causes dorsal wrist pain without a palpable external mass. These are a common cause of unexplained wrist pain in young adults and athletes, particularly originating from the scapholunate ligament or the dorsal capsule. Occult ganglia are invisible on physical examination and radiographs and can only be detected with MRI or high-resolution ultrasound. Confirming the diagnosis is important because it guides targeted treatment with aspiration or arthroscopic excision of the stalk and eliminates the need for extensive diagnostic workup for other wrist pathology. AI can help explain a report that mentions a small cyst, but it cannot confirm the diagnosis or exclude another cause of a lump.
How often do wrist ganglia recur after treatment?
A systematic review reported average recurrence rates of 59% after aspiration, 21% after open excision, and 6% after arthroscopic excision. These pooled results came from different studies; comparative trials did not establish that arthroscopy was superior. They describe recurrence after treatment, not an individual prediction or a reason by themselves to choose a procedure.
Sources
- Head L, Gencarelli JR, Allen M, Boyd KU. Wrist ganglion treatment: systematic review and meta-analysis. J Hand Surg Am. 2015;40(3):546-553.e8.
- Dias JJ, Dhukaram V, Kumar P. The natural history of untreated dorsal wrist ganglia and patient reported outcome 6 years after intervention. J Hand Surg Eur Vol. 2007;32(5):502-508.
- Zoller SD, Benner NR, Iannuzzi NP. Ganglions in the hand and wrist: advances in 2 decades. J Am Acad Orthop Surg. 2023;31(2):e58-e67.
- Goldsmith S, Yang SS. Magnetic resonance imaging in the diagnosis of occult dorsal wrist ganglions. J Hand Surg Eur Vol. 2008;33(5):595-599.
Understand your imaging before your next appointment
MRI, X-ray or CT from a CD, folder or ZIP. A PDF report or photos of the films work too.
Free to open and preview, no account needed. An optional AI report from $10 explains your images in plain language, with questions for your doctor.
Your raw files stay on this device. Only rendered images and minimal context are sent when you request an AI report.
Medical Disclaimer: This page is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. AI-generated analysis may contain errors. Always consult a qualified healthcare professional for medical decisions. Full Disclaimer