
Do You Need a 3T MRI for a Wrist Injury?
Learn when 3T wrist MRI can help for TFCC tears, scapholunate ligament injury, occult scaphoid fracture, and cartilage detail, and when X-ray or 1.5T MRI is enough.
Key Takeaways
- 3T wrist MRI can help with TFCC, intrinsic ligament, occult fracture, and marrow questions
- X-ray and CT remain important for fracture alignment and carpal bone detail
- MR arthrogram may be more relevant than magnet strength for some TFCC and ligament injuries
- Do not repeat imaging unless the new test can change splinting, therapy, injection, or surgery decisions
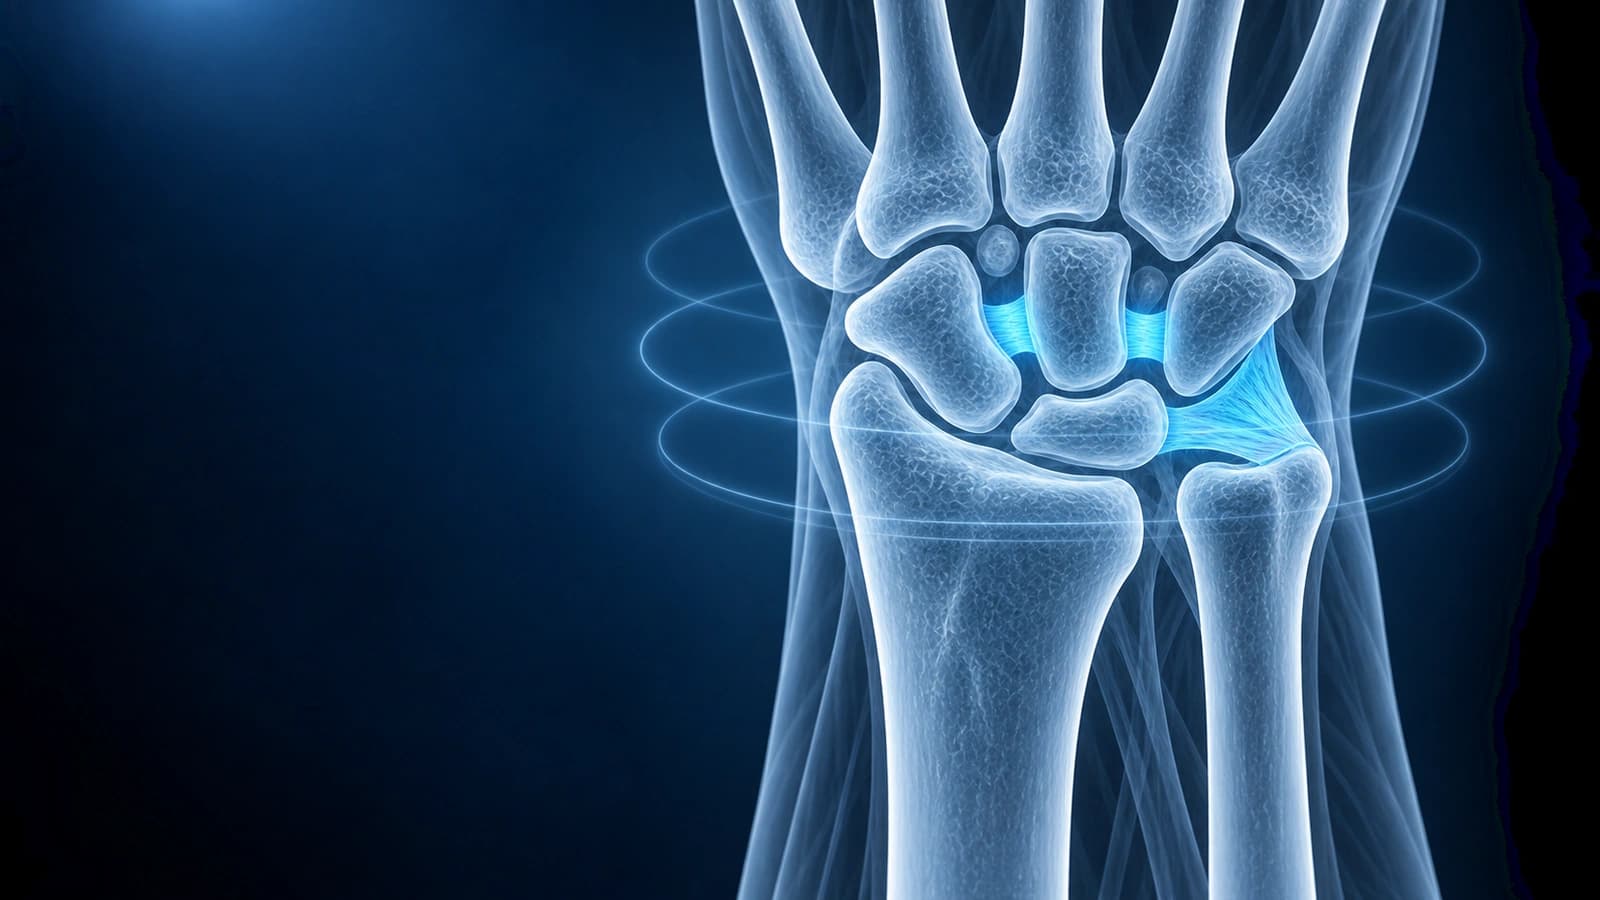
A 3T wrist MRI can be useful because the wrist is packed with tiny structures: TFCC fibers, scapholunate and lunotriquetral ligaments, cartilage, small carpal bones, and subtle marrow edema. But it is not the right first move for every painful wrist.
Wrist imaging is about matching the test to the question. X-ray may be enough for many fractures and arthritis patterns, CT can show carpal bone alignment, and MR arthrogram may beat a standard MRI for selected ligament or TFCC questions.
Quick Answer: When 3T Wrist MRI Is Worth Asking About
Ask about 3T when the decision depends on TFCC detail, intrinsic ligament tears, occult scaphoid fracture, early Kienbock disease, cartilage injury, or subtle marrow edema. Do not pay extra for 3T when X-ray, CT, ultrasound, or a recent clear MRI already answers the treatment question.
When 3T Can Add Value for Wrists
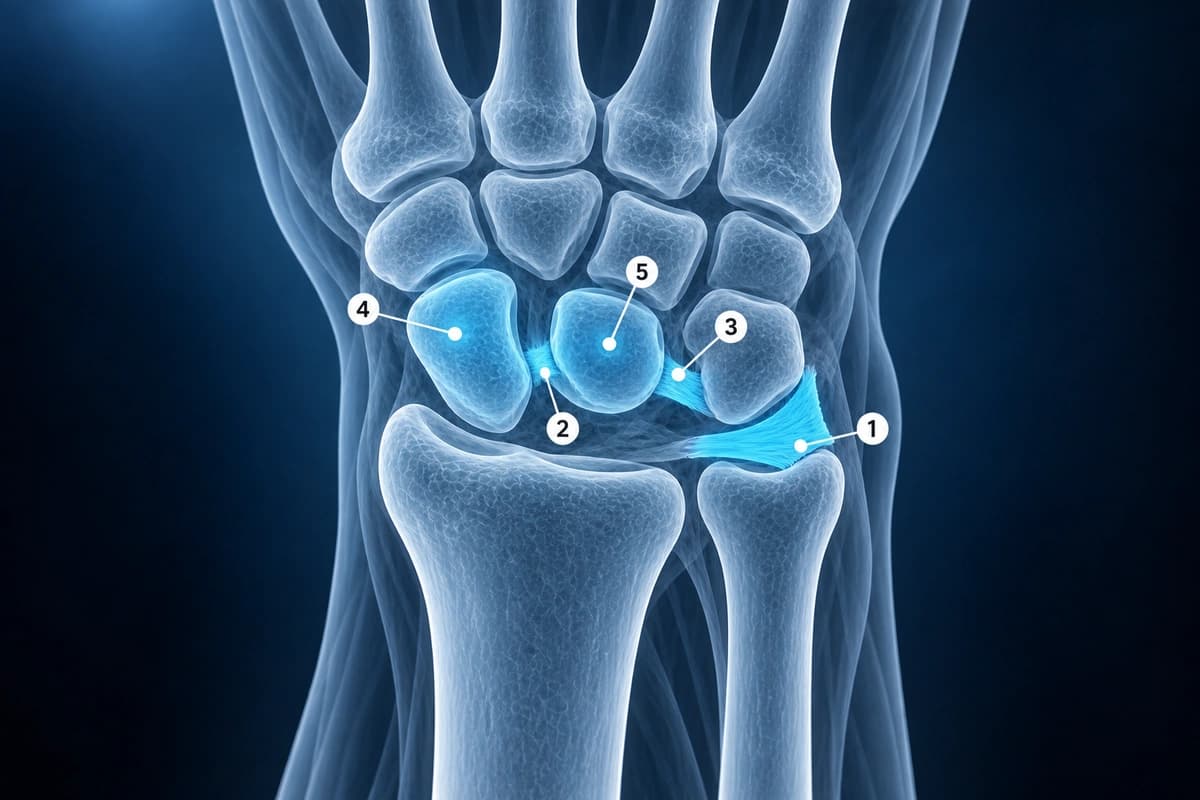
- TFCC tears where central versus peripheral detail may affect treatment
- Scapholunate or lunotriquetral ligament injury after a fall or twisting injury
- Occult scaphoid fracture or bone bruise after normal or unclear X-rays
- Kienbock disease, ulnar impaction, cartilage injury, or subtle carpal marrow edema
- Persistent pain where the report needs to separate tendon, ligament, cartilage, and bone causes
When You Probably Do Not Need 3T
- First imaging after most wrist trauma, where X-rays check fracture and alignment
- Known displaced fracture or carpal alignment problem where CT is needed for bone detail
- Classic de Quervain tenosynovitis or ganglion cyst when exam and ultrasound are enough
- Advanced arthritis already clear on X-ray
- Repeating a recent wrist MRI without a new specialist question
3T vs MR Arthrogram for TFCC and Ligament Questions
For selected TFCC or intrinsic ligament injuries, the question may be standard MRI versus MR arthrogram, not only 1.5T versus 3T. If scaphoid injury is the concern, read our occult scaphoid fracture protocol.
Frequently Asked Questions
Is 3T MRI necessary for a TFCC tear?
Not always. 3T can improve small-structure detail, but some TFCC questions are better answered by a dedicated wrist protocol or MR arthrogram.
Is 3T MRI better for occult scaphoid fracture?
It can be helpful, especially for marrow edema or a subtle fracture line after normal X-rays. The bigger issue is getting timely imaging with a dedicated wrist protocol so immobilization decisions are not delayed.
Should I repeat a 1.5T wrist MRI on 3T?
Repeat only if the first scan was technically limited or left a specific TFCC, ligament, scaphoid, or cartilage question unanswered. A stronger magnet alone is not a good reason to pay twice.
Sources
- Magee T. Comparison of 3-T MRI and arthroscopy of intrinsic wrist ligament and TFCC tears. AJR Am J Roentgenol. 2009;192(1):80-85.
- Smith TO, Drew B, Toms AP, et al. Diagnostic accuracy of magnetic resonance imaging and magnetic resonance arthrography for triangular fibrocartilaginous complex injury: a systematic review and meta-analysis. J Bone Joint Surg Am. 2012;94(9):824-832.
- Expert Panel on Musculoskeletal Imaging; Stensby JD, Fox MG, et al. ACR Appropriateness Criteria Chronic Hand and Wrist Pain: 2023 Update. J Am Coll Radiol. 2024;21(6S):S65-S78.
- Expert Panel on Musculoskeletal Imaging; Torabi M, Lenchik L, et al. ACR Appropriateness Criteria Acute Hand and Wrist Trauma. J Am Coll Radiol. 2019;16(5S):S7-S17.
Related Articles
Decode your wrist MRI report including TFCC evaluation, scaphoid fracture detection, and carpal tunnel findings.
Up to 20% of scaphoid fractures are missed on initial X-ray. MRI within 2 weeks rules out occult fracture and prevents non-union — when to ask for follow-up imaging.
Learn about common wrist conditions including TFCC tears, scaphoid fractures, carpal tunnel syndrome, de Quervain's, and ganglion cysts.
Related Conditions
Understand your imaging before your next appointment
MRI, X-ray or CT from a CD, folder or ZIP. A PDF report or photos of the films work too.
Free to open and preview, no account needed. An optional AI report from $10 explains your images in plain language, with questions for your doctor.
Your raw files stay on this device. Only rendered images and minimal context are sent when you request an AI report.
Medical Disclaimer: This page is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. AI-generated analysis may contain errors. Always consult a qualified healthcare professional for medical decisions. Full Disclaimer